



Clinical features of children with chest tightness variant asthma and diagnostic value of EOS count, total IgE and pulmonary function in peripheral blood
-
摘要:
目的 探讨儿童胸闷变异性哮喘(CTVA)的临床特征及外周血嗜酸性粒细胞(EOS)计数、总IgE、肺功能的诊断价值,为儿童CTVA的早期识别提供依据。 方法 以2023年1月—2024年12月在蚌埠医科大学第一附属医院就诊的51例CTVA患儿为研究对象,选取同期58例非急性发作期典型哮喘患儿为CA组,及40例健康儿童为对照组。收集3组临床资料,使用Spearman相关分析法研究外周血EOS计数、总IgE与肺功能的相关性,并绘制ROC曲线分析其对儿童CTVA的诊断价值。 结果 CTVA组发病年龄[10.3(8.8,11.6)岁]高于CA组[7.7(6.4,10.5)岁,Z=-3.811,P < 0.05];2组发病时间、发病季节、合并过敏性鼻炎史、BMI以及各项肺功能指标差异均无统计学意义。CTVA组外周血EOS计数、总IgE低于CA组,但高于对照组(P < 0.05)。CTVA组外周血EOS计数、总IgE均与小气道[最大呼气中期流速(MMEF)、用力呼气50%(FEF50)、75%(FEF75)肺活量的呼气峰流速]呈负相关关系(r < 0,P < 0.05)。ROC曲线显示,CTVA组MMEF、FEF50、FEF75的最佳截断值分别为76.4%、68.3%、67.1%,外周血EOS计数、总IgE最佳截断值为0.12×10⁹/L、62.6 IU/mL;外周血EOS计数+总IgE+三项小气道指标的AUC为0.832(95% CI: 0.731~0.907,P < 0.05),均大于单一指标的诊断效能。 结论 CTVA患儿的发病年龄高于CA患儿;外周血EOS计数、总IgE联合小气道可协助CTVA患儿的临床诊断。 Abstract:Objective To investigate the clinical characteristics of childhood chest tightness variant asthma (CTVA) and the diagnostic value of peripheral blood eosinophil (EOS) count, total IgE, and pulmonary function, so as to provide evidence for early identification of CTVA in children. Methods A total of 51 children with CTVA admitted to the First Affiliated Hospital of Bengbu Medical University from January 2023 to December 2024 were enrolled as the study subjects. In addition, 58 children with non-acute exacerbation typical asthma during the same period were selected as the CA group, and 40 healthy children served as the control group. Clinical data from the three groups were collected. Spearman correlation analysis was used to examine the correlations of peripheral blood EOS count and total IgE with pulmonary function parameters. Receiver operating characteristic (ROC) curves were plotted to analyze their diagnostic value for childhood CTVA. Results The age of onset in the CTVA group was 10.3 (8.8, 11.6) years, which was higher than that in the CA group [7.7 (6.4, 10.5) years, Z=-3.811, P < 0.05]. There were no statistically significant differences between the two groups in terms of disease duration, season of onset, history of comorbid allergic rhinitis, BMI, and various pulmonary function indices. The peripheral blood EOS count and total IgE in the CTVA group were lower than those in the CA group, but higher than those in the control group (P < 0.05). In the CTVA group, both peripheral blood EOS count and total IgE showed negative correlations with small airway parameters [maximal mid-expiratory flow (MMEF), forced expiratory flow at 50% of vital capacity (FEF50), forced expiratory flow at 75% of vital capacity (FEF75), r < 0, P < 0.05]. ROC curve analysis indicated that the optimal cutoff values for MMEF, FEF50, and FEF75 in the CTVA group were 76.4%, 68.3%, and 67.1%, respectively, while the optimal cutoff values for peripheral blood EOS count and total IgE were 0.12×10⁹/L and 62.6 IU/mL, respectively. The area under the curve (AUC) for the combination of peripheral blood EOS count, total IgE, and the three small airway indices was 0.832 (95% CI: 0.731-0.907, P < 0.05), which was greater than the diagnostic efficacy of any single indicator. Conclusion The age of onset in children with CTVA is higher than that in children with CA. The combination of peripheral blood EOS count, total IgE, and small airway parameters can assist in the clinical diagnosis of CTVA in children. -
Key words:
- Chest tightness variant asthma /
- Children /
- Pulmonary function /
- Immunoglobulin E /
- Eosinophils
-

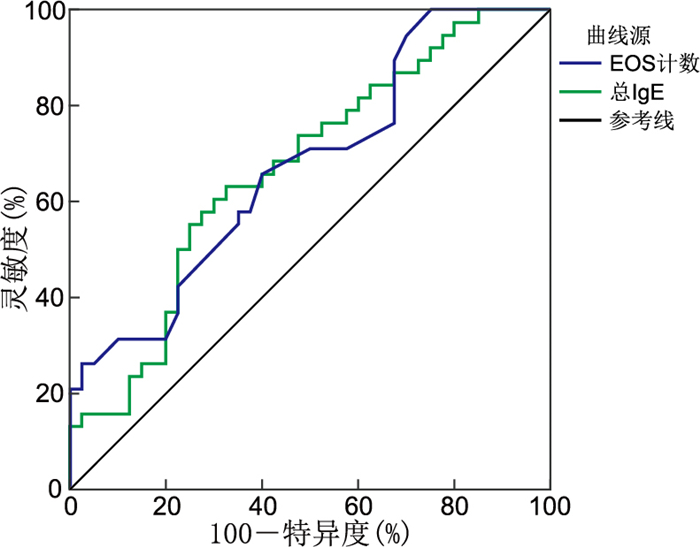
图 1 外周血EOS计数、总IgE预测儿童CTVA的ROC曲线
Figure 1. ROC curve of peripheral blood EOS count and total IgE in the prediction of CTVA in children

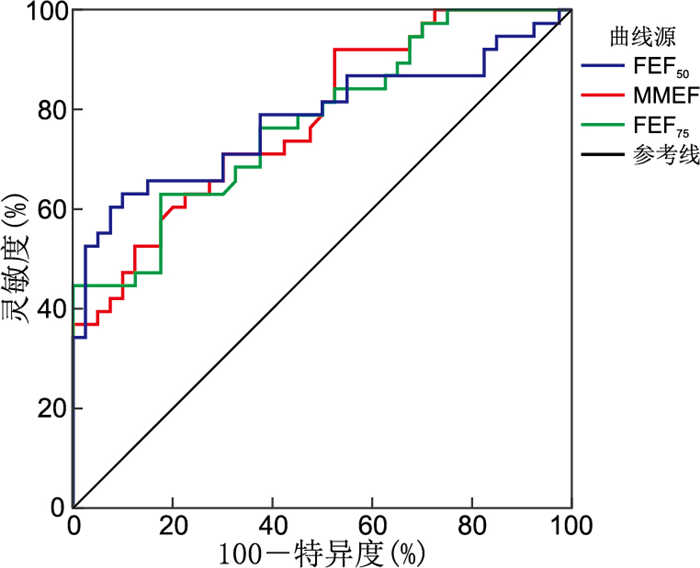
图 2 MMEF、FEF50、FEF75预测儿童CTVA的ROC曲线
Figure 2. ROC curves of MMEF, FEF50, and FEF75 in the prediction of CTVA in children

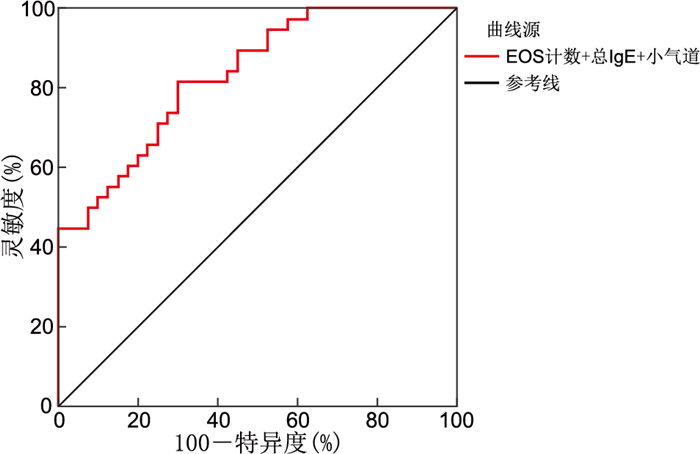
图 3 外周血EOS计数+总IgE+小气道指标预测儿童CTVA的ROC曲线
Figure 3. ROC curves for peripheral blood EOS counts combined with small airway indices and total IgE in the prediction of CTVA in children
表 1 CTVA组与CA组患儿临床资料比较
Table 1. Comparison of clinical features between the CTVA and CA groups
组别 例数 发病年龄
[M(P25,P75),岁]BMI
[M(P25,P75)]鼻炎史[例(%)] 有 无 CTVA组 51 10.3(8.8,11.6) 19.12(15.62,21.55) 33(64.7) 18(35.3) CA组 58 7.7(6.4,10.5) 16.92(14.69,21.12) 43(74.1) 15(25.9) 统计量 -3.811a -1.561a 1.144b P值 <0.001 0.119 0.285 组别 例数 发病时间[例(%)] 发病季节[例(%)] 白天 夜间 无规律 春 夏 秋 冬 CTVA组 51 18(35.3) 23(45.1) 10(19.6) 10(19.6) 20(39.2) 11(21.6) 10(19.6) CA组 58 13(22.4) 25(43.1) 20(34.5) 11(19.0) 19(32.8) 21(36.2) 7(12.1) 统计量 3.789b 3.292b P值 0.150 0.349 注:a为Z值,b为χ2值。  下载: 导出CSV
表 2 3组研究对象外周血EOS计数、总IgE比较
Table 2. Comparison of peripheral blood EOS counts and total IgE among the three groups
组别 例数 EOS计数
[M(P25, P75),×109/L]例数 总IgE
[M(P25, P75),IU/mL]CTVA组 45 0.170(0.095,0.275)a 38 72.70(30.48,183.00)a CA组 46 0.320(0.133,0.475)ab 31 264.00(82.00,544.00)ab 对照组 40 0.115(0.043,0.188) 40 36.95(14.83,71.70) H值 23.168 23.759 P值 <0.001 <0.001 注:与对照组比较,aP<0.05;与CTVA组比较,bP<0.05。
下载: 导出CSV
表 3 3组研究对象肺功能参数比较
Table 3. Comparison of pulmonary function parameters among the three groups of research subjects
组别 例数 FEV1
[M(P25, P75),%]FVC
[M(P25, P75),%]FEV1/FVC
[M(P25, P75)]PEF
[M(P25, P75),%]MMEF(x±s,%) FEF25
[M(P25, P75),%]FEF50(x±s,%) FEF75
[M(P25, P75),%]CTVA组 51 88.30(81.10,94.80)a 91.30(81.70,102.70) 96.80(89.00,103.60)a 74.00(68.10,82.50) 64.77±17.16a 70.60(64.60,80.20)a 65.72±21.77a 61.90(38.60,71.00)a CA组 56 87.20(80.28,98.90)a 91.70(84.35,104.00) 94.55(86.08,100.78)a 71.55(59.98,88.05) 61.39±21.53a 68.65(56.25,82.10)a 62.72±21.38a 53.25(36.18,66.03)a 对照组 40 98.80(91.50,105.60) 100.80(83.15,107.60) 102.80(97.48,108.00) 81.00(72.13,87.48) 83.26±15.78 84.70(75.93,93.90) 83.98±14.52 76.05(67.53,91.48) 统计量 23.851b 2.811b 20.698b 3.112b 17.730c 17.217b 14.830c 33.552b P值 < 0.001 0.245 < 0.001 0.211 < 0.001 < 0.001 < 0.001 < 0.001 注:与对照组比较,aP<0.05;b为H值,c为F值。
下载: 导出CSV
表 4 CTVA组外周血EOS计数、总IgE与肺功能指标的相关性
Table 4. Correlations between peripheral blood EOS count, total IgE, and pulmonary function indicators in the CTVA group
项目 外周血EOS计数 总IgE rs值 P值 rs值 P值 FEV1 -0.206 0.215 -0.146 0.381 FVC -0.075 0.653 -0.006 0.972 FEV1/FVC -0.127 0.446 -0.069 0.680 PEF -0.019 0.909 -0.127 0.446 MMEF -0.344 0.034 -0.834 < 0.001 FEF25 -0.163 0.327 -0.038 0.823 FEF50 -0.333 0.041 -0.793 < 0.001 FEF75 -0.368 0.023 -0.822 < 0.001
下载: 导出CSV
表 5 外周血EOS计数、总IgE、小气道指标及联合诊断CTVA的ROC曲线分析
Table 5. ROC curve for peripheral blood EOS, total IgE, small airway indices, and their combination in the diagnosis of CTVA
项目 截断值 灵敏度(%) 特异度(%) AUC 95% CI P值 MMEF 76.4 71.00 70.00 0.782 0.674~0.867 < 0.001 FEF50 68.3 63.16 90.00 0.780 0.672~0.866 < 0.001 FEF75 67.1 63.16 82.50 0.777 0.668~0.863 < 0.001 EOSa 0.12 65.79 60.00 0.674 0.559~0.776 0.004 总IgE 62.6 63.16 67.50 0.670 0.554~0.772 0.006 EOS+总IgE+小气道a 81.58 70.00 0.832 0.731~0.907 < 0.001 注:a小气道为MMEF+FEF50+FEF75。
下载: 导出CSV
-
[1] 中华医学会儿科学分会呼吸学组哮喘协作组, 中华医学会呼吸病学分会哮喘学组, 中国医药教育协会儿科专业委员会. 儿童胸闷变异性哮喘诊断与治疗专家共识[J]. 中华实用儿科临床杂志, 2023, 38(9): 641-646.Asthma Collaboration Group of the Respiratory Diseases Section of the Chinese Medical Association Pediatrics, Asthma Group of the Respiratory Diseases Section of the Chinese Medical Association, Pediatric Professional Committee of the Chinese Medical Education Association. Expert consensus on the diagnosis and treatment of chest tightness variant asthma in children[J]. Chinese Journal of Applied Clinical Pediatrics, 2023, 38(9): 641-646. [2] 陈璇, 曹卓, 李雨玲, 等. 成人胸闷变异性哮喘的临床特征及诊断思路[J]. 浙江临床医学, 2024, 26(1): 87-89.Chen X, Cao Z, Li Y L, et al. Clinical characteristics and diagnostic ideas of adult chest tightness variant asthma[J]. Zhejiang Clinical Medical Journal, 2024, 26(1): 87-89. [3] ZHU W, LIU C, SHA L, et al. Atypical asthma in children who present with isolated chest tightness: risk factors and clinical features[J]. J Asthma, 2022, 59(10): 1952-1960. doi: 10.1080/02770903.2021.1980583 [4] CHEN L, DUAN H, LI X, et al. The causes of chest pain in children and the criteria for targeted myocardial enzyme testing in identifying the causes of chest pain in children[J]. Front Cardiovasc Med, 2021, 8: 582129. DOI: 10.3389/fcvm.2021.582129. [5] 车鸾卿, 杜旭菲, 颜伏归, 等. 中国胸闷变异性哮喘临床研究回顾及启示[J]. 中华医学杂志, 2023, 103(34): 2639-2646.Che L Q, Du X F, Yan F G, et al. Review and perspective of clinical research involving chest tightness variant asthma in China[J]. National Medical Journal of China, 2023, 103(34): 2639-2646. [6] 中国医药教育协会儿科专业委员会, 中华医学会儿科学分会呼吸学组哮喘协作组, 中国医师协会呼吸医师分会儿科呼吸工作委员会, 等. 中国儿童支气管哮喘诊治现状及发展策略(2022)[J]. 中华实用儿科临床杂志, 2023, 38(9): 647-680.Pediatric Professional Committee of China Medical Education Association, Asthma Cooperative Group of Respiratory Study Group of Chinese Medical Association, Pediatric Respiratory Working Committee of Respiratory Physicians Branch of Chinese Medical Association, et al. Current situation and development strategies of diagnosis and treatment of bronchial asthma in children in China (2022)[J]. Chinese Journal of Applied Clinical Pediatrics, 2023, 38(9): 647-680 [7] 中华医学会呼吸病学分会哮喘学组. 胸闷变异性哮喘诊治中国专家共识[J]. 中华医学杂志, 2023, 103(34): 2662-2673.Chinese Medical Association of Respiratory Disease Branch Asthma Study Group. Expert consensus on the diagnosis and treatment of chest tightness variant asthma in China[J]. National Medical Journal of China, 2023, 103(34): 2662-2673. [8] 华雯, 殷菊, 张敏, 等. 中国儿科医师对胸闷变异性哮喘的认知和诊治现状调查[J]. 中华医学杂志, 2023, 103(34): 2727-2732.Hua W, Yin J, Zhang M, et al. Investigation on cognition, diagnosis and treatment status of chest tightness variant asthma among Chinese pediatricians[J]. National Medical Journal of China, 2023, 103(34): 2727-2732. [9] 陈嘉玲, 沙莉, 刘传合. 胸闷变异性哮喘的研究进展[J]. 中华预防医学杂志, 2023, 57(3): 327-332.Chen J L, Sha L, Liu C H. Research advances in chest tightness variant asthma[J]. Chinese Journal of Preventive Medicine, 2023, 57(3): 327-332. [10] 中华医学会儿科学分会呼吸学组, 中华儿科杂志编辑委员会, 中国医药教育协会儿科专业委员会. 儿童支气管哮喘诊断与防治指南(2025)[J]. 中华儿科杂志, 2025, 63(4): 324-337.Respiratory Group of the Pediatrics Branch of the Chinese Medical Association, Editorial Committee of the Chinese Journal of Pediatrics, Pediatric Professional Committee of the Chinese Medical Education Association. Guidelines for the diagnosis and optimal management of asthma in children (2025)[J]. Chinese Journal of Pediatrics, 2025, 63(4): 324-337. [11] TAO Z, ZHU H, ZHANG J, et al. Recent advances of eosinophils and its correlated diseases[J]. Front Public Health, 2022, 10: 954721. DOI: 10.3389/fpubh.2022.954721. [12] CHULKOV V, ELENA M, MEDVEDEVA L, et al. The clinical relevance of differential cell counts in induced sputum and its relationship with various forms of asthma[J]. Curr Respir Med Rev, 2021, 17(2): 69-77. doi: 10.2174/1573398X17666210611091246 [13] 陈嘉玲, 宋欣, 朱雯靓, 等. 儿童胸闷变异性哮喘的临床特征及危险因素分析[J]. 中华预防医学杂志, 2024, 58(6): 815-822.Chen J L, Song X, Zhu W L, et al. Analysis of clinical characteristics and risk factors of chest tightness variant asthma in children[J]. Chinese Journal of Preventive Medicine, 2024, 58(6): 815-822. [14] 宋欣, 李硕, 朱雯靓, 等. 儿童胸闷变异性哮喘肺功能改变的特征[J]. 中华临床免疫和变态反应杂志, 2020, 14(1): 27-32.Song X, Li S, Zhu W L. Characteristics of pulmonary function in children with chest tightness variant asthma[J]. Chinese Journal of Allergy & Clinical Immunology, 2020, 14(1): 27-32. [15] 楚辉, 高玮. 成人不典型哮喘误诊漏诊原因分析[J]. 河北医药, 2021, 43(17): 2618-2620, 2624.Chu H, Gao W. Analysis for the cause of misdiagnosis or missed diagnosis of adults with atypical asthma[J]. Hebei Medical Journal, 2021, 43(17): 2618-2620, 2624. [16] 柴小艺, 冯雍, 蔡栩栩. 肺功能小气道功能评价在儿童哮喘中的应用进展[J]. 国际儿科学杂志, 2022, 49(4): 254-257.Chai X Y, Feng Y, Cai X X. Application progress of small airway function assessed by lung function testing in children with asthma[J]. International Journal of Pediatrics, 2022, 49(4): 254-257. [17] HAN J, LI L, GONG Y, et al. Small airway inflammation in atypical asthma[J]. Heliyon, 2024, 10(17): e36124. DOI: 10.1016/j.heliyon.2024.06.135. [18] HANIBUCHI M, MITSUHASHI A, KAJIMOTO T, et al. A case of chest tightness variant asthma: the usefulness of fractional exhaled nitric oxide as a marker for the diagnosis and clinical improvement[J]. J Med Invest, 2021, 68(3-4): 389-392. [19] FENG Y, ZHANG S, SHANG Y, et al. The use of exercise challenge testing and fractional exhaled nitric oxide in diagnosis of chest tightness variant asthma in children[J]. Int Arch Allergy Immunol, 2022, 183(7): 762-769. doi: 10.1159/000522062 [20] 张明强, 郭文佳, 徐文帅, 等. 胸闷变异性哮喘患者肺功能及炎症特点[J]. 南京医科大学学报(自然科学版), 2023, 43(2): 225-229, 262.Zhang M Q, Guo W J, Xu W S, et al. The characteristics of pulmonary function and inflammation in patients with chest tightness variant asthma[J]. Journal of Nanjing Medical University(Natural Sciences), 2023, 43(2): 225-229, 262. [21] 冯琴, 唐川婷, 侯小燕, 等. 缓解期支气管哮喘患儿血清NLR、IgE及25-(OH)D3水平与肺功能的相关性[J]. 贵州医科大学学报, 2021, 46(5): 573-577.Feng Q, Tang C T, Hou X Y, et al. Correlation between the levels of serum NLR, IgE, and 25-(OH)D3 with lung function of bronchial asthma children during remission[J]. Journal of Guizhou Medical University, 2021, 46(5): 573-577. [22] 王莉洁, 张明强, 赵丽娜, 等. 不同亚型支气管哮喘的气道炎症和肺功能特点分析[J]. 内蒙古医科大学学报, 2023, 45(5): 523-527.Wang L J, Zhang M Q, Zhao L N, et al. Analysis of airway inflammation and pulmonary function characteristics in different subtypes of bronchial asthma[J]. Journal of Inner Mongolia Medical University, 2023, 45(5): 523-527. [23] 王颖, 云春梅, 刘柯含, 等. 支气管哮喘不同炎症表型的临床特征分析[J]. 中华全科医学, 2022, 20(12): 2055-2058, 2091. doi: 10.16766/j.cnki.issn.1674-4152.002768Wang Y, Yun C M, Liu K H, et al. Clinical characteristic analysis of different inflammatory phenotypes in bronchial asthma[J]. Chinese Journal of General Practice, 2022, 20(12): 2055-2058, 2091. doi: 10.16766/j.cnki.issn.1674-4152.002768
 点击查看大图
计量
- 文章访问数: 9
- HTML全文浏览量: 3
- PDF下载量: 0
- 被引次数: 0
