



Analysis of pregnancy outcomes and predictive factors for miscarriage risk after transvaginal multifetal pregnancy reduction
-
摘要:
目的 评估经阴道超声引导多胎妊娠减胎术(TV-MFPR)的安全性和影响因素。 方法 回顾性分析2018年3月—2024年5月在安徽医科大学第一附属医院行辅助生殖技术获双胎以上妊娠共338例行减胎术产妇,按结局、流产原因及三胎存活数分组比较临床指标,行logistic回归分析研究减胎后流产的影响因素。 结果 根据减胎后结局分为流产组(LC,36例)和活产组(FM,302例),LC组减胎胎龄[65.00(61.00, 70.50)d vs. 61.00(60.00, 64.00)d,Z=-3.475, P<0.001]及KCL使用率[15例(41.7%)vs.40例(13.2%),P<0.001]均高于FM组。Logistic回归分析显示,KCL用药(OR=0.318,P=0.009)、BMI每增加1单位(OR=0.895,P=0.022)及减胎胎龄每延迟1 d(OR=0.946,P=0.032)均升高流产风险。存活一胎组移植2枚胚胎比例及单卵双胎率均显著高于二胎组(P<0.05)。活产组中双胎分娩并发症发生率显著高于单胎。 结论 TV-MFPR是ART后多胎妊娠的安全有效干预手段。建议7~9周早期减胎,控制BMI,慎用KCL。双胎妊娠并发症风险高,需个体化选择减胎方案,优化妊娠结局。 Abstract:Objective To evaluate the safety and influencing factors of transvaginal ultrasound-guided multiple pregnancy reduction procedure (TV-MFPR). Methods A retrospective analysis was conducted on 338 pregnant women who underwent reduction surgery for multiple pregnancies after assisted reproductive technology at the First Affiliated Hospital of Anhui Medical University from March 2018 to May 2024. The clinical indicators were compared among groups based on the outcome, cause of miscarriage, and the number of surviving triplets. Logistic regression analysis of risk factors influencing miscarriage after reduction. Results Divided into the miscarriage group (LC, 36 cases) and the live birth group (FM, 302 cases) based on outcomes after reduction. The gestational age at reduction of the LC group [65.00 (61.00, 70.50) days vs. 61.00 (60.00, 64.00) days, Z=-3.475, P < 0.001], and the usage rate of KCL [15 cases (41.7%) vs. 40 cases (13.2%), P < 0.001] were all higher than those of the FM group. Logistic regression showed that the use of KCL (OR=0.318, P=0.009), each unit increase in BMI (OR=0.895, P= 0.022), and each delay of gestational age in reduction (OR=0.946, P=0.032) all increased the risk of miscarriage. The proportion of transferring two embryos in the single-embryo survival group and the rate of monozygotic twins were both significantly higher than those in the twin pregnancy group (P < 0.05). The incidence of complications during twin delivery was significantly higher in the live birth group than in the singleton group. Conclusion TV-MFPR is a safe and effective intervention method for multiple pregnancies after ART. It is recommended to perform early reduction at 7-9 weeks, control BMI, and use KCL with caution. The risk of complications in twin pregnancies is high, and individualized selection of reduction schemes and optimization of pregnancy outcomes are necessary. -

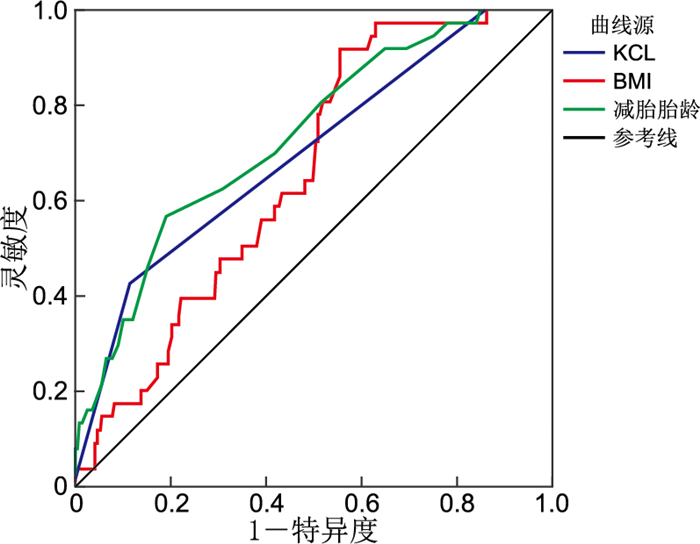
图 1 BMI、KCL、减胎胎龄预测减胎后流产的ROC曲线
Figure 1. ROC curves of BMI, KCL, and gestational age at fetal reduction for predicting post-reduction miscarriage
表 1 2组减胎患者减胎结局及临床资料比较
Table 1. Comparison of pregnancy outcomes and clinical data between two fetal reduction groups
组别 例数 年龄(x±s,岁) BMI[M(P25, P75)] 活产史[例(%)] 移植胚胎数[M(P25, P75),个] 孕囊数[M(P25, P75),个] 胚芽数[M(P25, P75),个] 减胎数[M(P25, P75),个] KCL[例(%)] 减胎胎龄[M(P25, P75),d] LC组 36 33.39±4.09 22.49(21.08, 24.92) 17(47.2) 2.00(2.00, 2.00) 2.00(2.00, 2.00) 2.00(2.00, 3.00) 1.00(1.00, 1.00) 15(41.7) 65.00(61.00, 70.50) FM组 302 32.62±4.13 21.85(19.70, 24.24) 105(34.8) 2.00(2.00, 2.00) 2.00(2.00, 2.00) 2.00(2.00, 3.00) 1.00(1.00, 1.00) 40(13.2) 61.00(60.00, 64.00) 统计量 1.059a -1.960b 2.163c -0.341b -0.737b -0.794b -1.624b 19.071c -3.475b P值 0.290 0.050 0.141 0.733 0.461 0.427 0.104 <0.001 <0.001 注:a为t值,b为Z值,c为χ2值。  下载: 导出CSV
表 2 3组流产患者临床资料比较
Table 2. Comparison of clinical characteristics among three groups of miscarriage patients
组别 例数 年龄(x±s,岁) BMI[M(P25, P75)] 活产史[例(%)] 移植胚胎数[M(P25, P75),个] 孕囊数[M(P25, P75),个] 胚芽数[M(P25, P75),个] JL组 12 33.33±2.57 21.72 (21.07, 24.22) 6(50.0) 2.00(2.00, 2.00) 2.00(2.00, 2.00) 2.00(2.00, 3.00) PS组 19 33.26±4.98 22.27 (21.02, 25.50) 9(47.4) 2.00(2.00, 2.00) 2.00(2.00, 2.00) 2.00(2.00, 3.00) QT组 5 34.00±4.00 23.37 (23.31, 24.45) 2(40.0) 2.00(2.00, 2.00) 2.00(2.00, 2.00) 2.00(2.00, 3.00) 统计量 0.062a 1.510b 0.142c 0.865b 3.993b 0.245b P值 0.940 0.471 0.931 0.649 0.136 0.885 组别 例数 减胎数[M(P25, P75),个] 存活数[M(P25, P75),个] KCL[例(%)] 减胎胎龄[M(P25, P75),d] 流产孕周[M(P25, P75),周] JL组 12 1.00(1.00, 1.00) 1.00(1.00, 1.00) 6(50.0) 65.0(62.00, 66.00) 11.00(8.00, 13.75) PS组 19 1.00(1.00, 1.00) 1.00(1.00, 1.00) 8(42.1) 65.0(60.00, 69.00) 20.00(19.00, 23.00) QT组 5 1.00(1.00, 1.00) 1.00(1.00, 1.00) 1(20.0) 71.0(62.00, 73.50) 21.00(17.50, 22.00) 统计量 2.257b 7.808b 1.310c 1.211b 21.009b P值 0.324 0.020 0.519 0.546 <0.001 注:a为F值,b为H值,c为χ2值。
下载: 导出CSV
表 3 三胎妊娠患者临床资料比较
Table 3. Comparison of clinical characteristics in triplet pregnancy patients
组别 例数 年龄(x±s,岁) BMI[M(P25, P75)] 移植胚胎数[M(P25, P75),个] 孕囊数[M(P25, P75),个] 胚芽数[M(P25, P75),个] 减胎数[M(P25, P75),个] KCL[例(%)] 减胎胎龄[M(P25, P75),d] 妊娠结局[例(%)] CY组 55 31.56±3.34 22.67(20.70, 24.23) 2.00(2.00, 2.00) 2.00(2.00, 2.00) 3.00(3.00, 3.00) 1.00(1.00, 1.00) 10(18.2) 62.00(60.00, 65.00) 51(92.7) CE组 54 31.61±4.03 22.11(20.25, 24.88) 2.00(2.00, 2.00) 2.00(2.00, 3.00) 3.00(3.00, 3.00) 1.00(1.00, 1.00) 9(16.7) 60.00(59.00, 64.25) 51(94.4) 统计量 0.067a -0.082b 1.910b -5.268b <0.001b <0.001b 0.043c -0.972b 0.134c P值 0.947 0.935 0.056 <0.001 0.999 0.999 0.835 0.331 0.715 注:a为t值,b为Z值,c为χ2值。
下载: 导出CSV
表 4 减胎后流产影响因素的二元logistic回归分析
Table 4. Binary logistic regression analysis of factors influencing miscarriage after fetal reduction
变量 B SE Waldχ2 P值 OR值 95% CI BMI -0.111 0.049 5.249 0.022 0.895 0.813~0.984 KCL -1.145 0.440 6.779 0.009 0.318 0.134~0.753 减胎胎龄 -0.055 0.026 4.602 0.032 0.946 0.899~0.995 注:各变量赋值如下,减胎后流产=1,妊娠=0;KCL,是=1,否=0;BMI、减胎胎龄为连续性变量,以实际值赋值。
下载: 导出CSV
-
[1] DAHDOUH E M, ZREIK T G, GHNANME W, et al. Prevention of multiple pregnancies in gonadotropin-insemination cycles[J]. Curr Opin Obstet Gynecol, 2022, 34(3): 101-106. doi: 10.1097/GCO.0000000000000777 [2] 王凤英, 章翀, 尹宗智, 等. 跨专业共享决策在双胎妊娠孕妇中的应用研究[J]. 中华全科医学, 2025, 23(2): 198-202. doi: 10.16766/j.cnki.issn.1674-4152.003866Wang F Y, Zhang C, Yin Z Z, et al. Application of interprofessional shared decision-making in pregnant women with twin pregnancies[J]. Chinese Journal of General Practice, 2025, 23(2): 198-202. doi: 10.16766/j.cnki.issn.1674-4152.003866 [3] PATUZZO M S, CASPRINI C, BOSCO M, et al. Voluntary multifetal pregnancy reduction: who should decide and select and why?[J]. Eur J Obstet Gynecol Reprod Biol, 2025, 308(4): 143-146. [4] 冯银宏, 钱晶晶, 宋学军. 孕前体重指数、孕期体重增加与妊娠期并发症及妊娠结局的关系[J]. 中国现代医学杂志, 2021, 31(2): 92-96.Feng Y H, Qian J J, Song X J. Relationship between pre-pregnancy body mass index, gestational weight gain and pregnancy complications/pregnancy outcomes[J]. Chin J Mod Med, 2021, 31(2): 92-96. [5] PINBORG A, WENNERHOLM U B, BERGH C. Long-term outcomes for children conceived by assisted reproductive technology[J]. Fertil Steril, 2023, 120(3 Pt 1): 449-456. [6] CHEN Z, XIONG L, JIN H, et al. Advanced maternal age causes premature placental senescence and malformation via dysregulated α-Klotho expression in trophoblasts[J]. Aging Cell, 2021, 20(7): e13417. DOI: 10.1111/acel.13417. [7] 曹佳城, 肖扬, 王素霞. 多囊卵巢综合征不孕患者药物促排卵的风险与防治进展[J]. 中华全科医学, 2023, 21(5): 844-848. doi: 10.16766/j.cnki.issn.1674-4152.002997Cao J C, Xiao Y, Wang S X. Risks and prevention advances in drug-induced ovulation for infertile patients with polycystic ovary syndrome[J]. Chin J Gen Pract, 2023, 21(5): 844-848. doi: 10.16766/j.cnki.issn.1674-4152.002997 [8] XIA S, YOU K, LIN M, et al. Intertwin nuchal translucency difference predicts the chance of co-twin death after fetal reduction in dichorionic triplet pregnancies: a retrospective analysis study[J]. BMC Pregnancy Childbirth, 2023, 23(1): 747. DOI: 10.1186/s12884-023-06064-9. [9] 张红霞, 杨锐, 杨松, 等. 经颅胸内注射KCl对胎儿复位的影响[J]. 北京大学学报, 2022, 54(5): 943-947.Zhang H X, Yang R, Yang S, et al. Effects of transvaginal intrathoracic KCl injection on fetal reduction[J]. J Peking Univ(Health Sci), 2022, 54(5): 943-947. [10] LIU S, LI G, WANG C, et al. Pregnancy and obstetric outcomes of dichorionic and trichorionic triamniotic triplet pregnancy with multifetal pregnancy reduction: a retrospective analysis study[J]. BMC Pregnancy Childbirth, 2022, 22(1): 280. DOI: 10.1186/s12884-022-04617-y. [11] 从艳艳, 沈曦, 匡延平. 高龄女性冻融胚胎移植中单个或双卵裂期胚胎与单个囊胚的活产率比较及相关影响因素[J]. 诊断学理论与实践, 2020, 19(1): 50-54.Cong Y Y, Shen X, Kuang Y P. Comparison of live birth rates and influencing factors between single/double cleavage-stage embryos and single blastocyst in frozen-thawed embryo transfer for advanced-age women[J]. Journal of Diagnostics Concepts & Practice, 2020, 19(1): 50-54. [12] LI N, SUN J, WANG J, et al. Selective termination of the fetus in multiple pregnancies using ultrasound-guided radiofrequency ablation[J]. BMC Pregnancy Childbirth, 2021, 21(1): 821. DOI: 10.1186/s12884-021-04285-4. [13] 张轶乐, 孙莹璞, 苏迎春, 等. 早期与中期多胎妊娠减胎术妊娠结局分析[J]. 中华全科医学, 2011, 9(9): 1365-1366, 1461.Zhang Y L, Sun Y P, Su Y C, et al. Pregnancy outcomes analysis of multifetal pregnancy reduction in early versus mid-trimester[J]. Chin J Gen Pract, 2011, 9(9): 1365-1366, 1461. [14] XU Q, LI M, WANG X, et al. Dichorionic triamniotic triplets after two blastocysts transfer underwent multifetal pregnancy reduction: two case reports and literature review[J]. BMC Womens Health, 2024, 24(1): 492. DOI: 10.1186/s12905-024-03324-4. [15] 任建枝, 沙爱国, 郑仁瑞, 等. 选择性减胎术在多胎妊娠中的应用[J]. 中国现代医学杂志, 2003, 13(11): 137-142.Ren J Z, Sha A G, Zheng R R, et al. Application of selective fetal reduction in multifetal pregnancies[J]. China Journal of Modern Medicine, 2003, 13(11): 137-142.
 点击查看大图
计量
- 文章访问数: 7
- HTML全文浏览量: 4
- PDF下载量: 1
- 被引次数: 0
