



Correlation of traditional Chinese medicine syndrome types of rheumatoid arthritis with plasma albumin and Th17/Treg related cytokines
-
摘要:
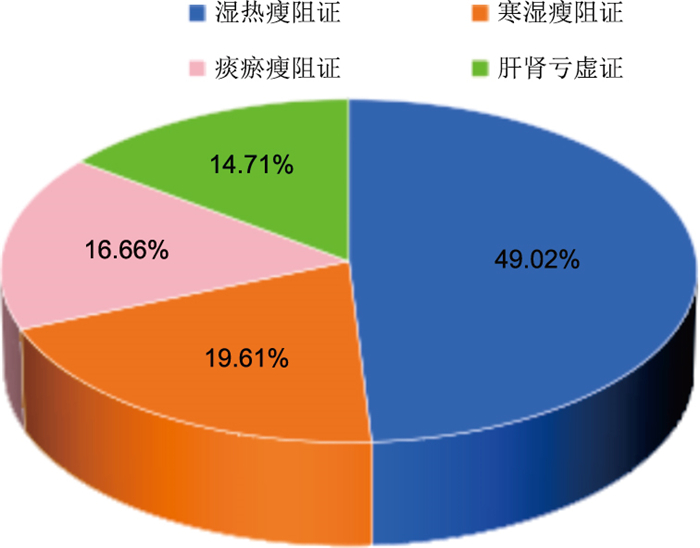
目的 研究类风湿性关节炎(RA)中医证型与血浆白蛋白(ALB)及Treg、辅助性T细胞17/调节性T细胞(Th17/Treg)相关细胞因子的相关性。 方法 选取2023年4月—2025年5月邯郸市中医院收治的102例RA患者及对照组(50例健康体检者),分析Th17/Treg相关细胞因子、ALB及与中医证型的关系。 结果 湿热痹阻证、寒湿痹阻证、痰瘀痹阻证、肝肾亏虚证分别50、20、17、15例;RA组Th17、白介素-17(IL-17)、白介素-23(IL-23)高于对照组(P<0.05),而调节性T细胞(Treg)、血浆ALB低于对照组(P<0.05);RA患者Th17、IL-17、IL-23、类风湿性关节炎疾病活动评分(DAS28)呈正相关关系,ALB与细胞因子呈负相关关系(P<0.05);RA患者寒湿痹阻证、肝肾亏虚证Th17更低(P<0.05),寒湿痹阻证、肝肾亏虚证IL-17、IL-23更高(P<0.05),肝肾亏虚证ALB最低(P<0.05);湿热痹阻证DAS28评分>5.1比例最高,肝肾亏虚证DAS28评分在3.3~5.0比例最高(P<0.05);湿热痹阻证、寒湿痹阻证、痰瘀痹阻证VAS评分更高,关节肿胀数、关节压痛数更多,血沉、CRP更高(P<0.05)。 结论 RA患者中医证型与ALB及Th17/Treg平衡、相关细胞因子有关,需开展针对性中医治疗。 Abstract:Objective To study the correlation of the traditional Chinese medicine (TCM) syndrome types of rheumatoid arthritis (RA) with plasma albumin (ALB) and helper T cell 17/regulatory T cell (Th17/Treg) related cytokines. Methods A total of 102 RA patients (RA group) and 50 healthy individuals undergoing physical examinations during the same period (control group) were selected as the research subjects. The relationships between Th17/Treg-related cytokines, ALB, and the traditional Chinese medicine syndrome types were analyzed. Results There were 50 cases of damp-heat obstruction syndrome, 20 cases of cold-dampness obstruction syndrome, 17 cases of phlegm-stasis obstruction syndrome, and 15 cases of liver-kidney deficiency syndrome. The levels of Th17, interleukin-17 (IL-17) and IL-23 in the RA group were higher than those in the control group (P < 0.05), while regulatory T cells (Treg) and plasma ALB were lower (P < 0.05). Th17, IL-17, IL-23 and the rheumatoid arthritis disease activity score (DAS28) score in RA patients were positively correlated pairwise, while ALB was significantly negatively correlated with the scores of Th17, IL-17, IL-23 and DAS28 (P < 0.05). In RA cases, Th17 in cold-dampness obstruction syndrome and liver-kidney deficiency syndrome was lower than that in damp-heat obstruction syndrome and phlegm-stasis obstruction syndrome (P < 0.05), while IL-17 and IL-23 were higher (P < 0.05), ALB was the lowest in liver-kidney deficiency syndrome, followed by damp-heat obstruction syndrome (P < 0.05). The proportions of DAS28 scores >5.1 were the highest in damp-heat obstruction syndrome. The proportion of DAS28 score ranging from 3.3 to 5.0 was the highest in patients with liver-kidney deficiency syndrome (P < 0.05). Compared with the syndrome of liver -kidney deficiency, the VAS scores of damp-heat obstructions syndrome, cold-dampness obstruction syndrome and phlegm-stasis obstruction syndrome were higher, the number of joint swellings and joint tenderness was more, and the levels of erythrocyte sedimentation rate (ESR) and C-reactive protein (CRP) were higher (P < 0.05). Conclusion The TCM syndrome types of RA patients are correlated with ALB, Th17/Treg balance, and related cytokines, necessitating targeted TCM treatment. -
Key words:
- Rheumatoid arthritis /
- Traditional Chinese medicine syndrome types /
- Albumin /
- Th17/Treg /
- Cytokine /
- Correlation
-

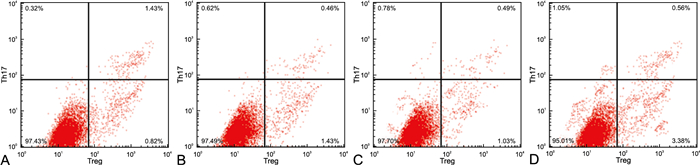
图 2 RA组及对照组Th17、Treg细胞比例(流式细胞技术)
注:A、B为RA患者Th17、Treg细胞比例,C、D为对照组患者Th17、Treg细胞比例。
Figure 2. Proportions of Th17 and Treg cells in the RA group and the control group (flow cytometry)
表 1 不同中医证型的RA患者基线资料比较
Table 1. Comparison of baseline data of RA patients with different TCM syndrome types
中医证型 例数 性别[例(%)] 年龄(x±s,岁) RA病程(x±s,年) 男性 女性 湿热痹阻证 50 27(54.00) 23(46.00) 54.26±5.57 4.25±0.46 寒湿痹阻证 20 12(60.00) 8(40.00) 55.10±5.56 4.30±0.44 痰瘀痹阻证 17 9(52.94) 8(47.06) 54.93±5.68 4.47±0.45 肝肾亏虚证 15 8(53.33) 7(46.67) 55.02±5.59 4.38±0.42 统计量 0.268a 0.161b 1.137b P值 0.966 0.923 0.338 注:a为χ2值,b为F值。  下载: 导出CSV
表 2 RA组与对照组Th17/Treg相关细胞因子、ALB水平比较(x±s)
Table 2. Comparison of Th17/ Treg-related cytokines and ALB levels between the RA group and the control group (x±s)
中医证型 例数 Th17 (%) IL-17 (pg/mL) IL-23 (pg/mL) Treg (%) ALB (g/L) RA组 102 2.25±0.58 101.47±33.83 84.74±31.46 1.89±0.23 34.44±3.87 对照组 50 1.52±0.07 53.21±5.48 26.77±2.89 3.94±0.45 38.46±4.14 t值 8.705 10.007 12.981 37.223 5.880 P值 <0.001 <0.001 <0.001 <0.001 <0.001
下载: 导出CSV
表 3 RA患者Th17相关细胞因子、ALB水平与DAS28评分的相关性(r值)
Table 3. The correlation between Th17-related cytokines and ALB levels in RA patients and the DAS28 score (r value)
项目 Th17 IL-17 IL-23 Treg ALB DAS28评分 Th17 1.000 IL-17 0.647a 1.000 IL-23 0.526a 0.488a 1.000 Treg -0.136 -0.143 -0.158 1.000 ALB -0.433a -0.502a -0.497a 0.089 1.000 DAS28评分 0.514a 0.493a 0.516a -0.177 -0.475a 1.000 注:aP<0.05。
下载: 导出CSV
表 4 各中医证型的RA患者Th17/Treg相关细胞因子、ALB水平比较(x±s)
Table 4. Comparison of Th17/Treg-related cytokines and ALB levels of RA patients with different TCM syndrome types (x±s)
中医证型 例数 Th17(%) IL-17(pg/mL) IL-23(pg/mL) Treg(%) ALB(g/L) 湿热痹阻证 50 2.83±0.29 70.46±7.35 55.67±5.84 1.84±0.26 33.69±3.57 寒湿痹阻证 20 1.72±0.19a 146.27±14.53a 125.63±12.75a 1.96±0.21a 35.78±3.64 痰瘀痹阻证 17 1.95±0.21ab 94.68±9.57ab 76.38±7.82ab 1.93±0.20ab 36.72±3.71a 肝肾亏虚证 15 1.70±0.18ac 119.60±12.31abc 105.44±10.73abc 1.87±0.18abc 31.64±3.26bc F值 154.712 392.712 471.698 1.564 7.033 P值 <0.001 <0.001 <0.001 0.203 <0.001 注:与湿热痹阻证比较,aP<0.05;与寒湿痹阻证比较,bP<0.05;与痰瘀痹阻证比较,cP<0.05。
下载: 导出CSV
表 5 各中医证型的RA患者DAS28评分及构成
Table 5. DAS28 scoring results and composition of RA patients with different TCM syndrome types
中医证型 例数 DAS28评分(x±s,分) >5.1分[例(%)] 3.3~5.0分[例(%)] 2.6~3.2分[例(%)] <2.6分[例(%)] 湿热痹阻证 50 6.02±0.64 49(98.00) 1(2.00) 0 0 寒湿痹阻证 20 5.29±0.53a 12(60.00) 8(40.00) 0 0 痰瘀痹阻证 17 5.16±0.54a 13(76.47) 4(23.53) 0 0 肝肾亏虚证 15 4.39±0.48abc 4(26.66) 10(66.67) 1(6.67) 0 统计量 34.183d 39.425e P值 <0.001 <0.001 注:与湿热痹阻证比较,aP<0.05;与寒湿痹阻证比较,bP<0.05;与痰瘀痹阻证比较,cP<0.05。d为F值,e为χ2值。
下载: 导出CSV
表 6 各中医证型的RA患者症状及实验室指标比较(x±s)
Table 6. Comparison of Symptoms and laboratory indicators of RA patients with different TCM syndrome types (x±s)
中医证型 例数 VAS评分(分) 关节肿胀数(个) 关节压痛数(个) ESR (mm/h) CRP (mg/L) RF (RU/mL) 抗CCP抗体(RU/mL) 湿热痹阻证 50 4.35±0.46 4.28±0.43 9.32±0.98 49.35±5.16 37.56±3.89 384.75±39.66 426.35±43.88 寒湿痹阻证 20 6.37±0.65a 3.72±0.38a 8.47±0.85a 35.73±3.67a 34.12±3.57a 377.89±38.37 418.34±42.39 痰瘀痹阻证 17 6.04±0.63a 2.68±0.29ab 7.31±0.76ab 46.37±4.38ab 42.67±4.35ab 380.55±38.94 422.73±42.68 肝肾亏虚证 15 3.28±0.29abc 1.78±0.16abc 5.43±0.56abc 32.14±3.25abc 30.19±3.16abc 379.72±38.41 424.38±43.56 F值 150.851 210.552 84.507 80.913 32.330 0.181 0.168 P值 <0.001 <0.001 <0.001 <0.001 <0.001 0.909 0.918 注:与湿热痹阻证比较,aP<0.05;与寒湿痹阻证比较,bP<0.05;与痰瘀痹阻证比较,cP<0.05。
下载: 导出CSV
-
[1] LIU L, DENG D, LI C, et al. The combination of modified acupuncture needle and melittin hydrogel as a novel therapeutic approach for rheumatoid arthritis treatment[J]. J Nanobiotechnology, 2024, 22(1): 432. DOI: 10.1186/s12951-024-02722-y. [2] 胡皖华, 胥义周, 白正林, 等. 巨噬细胞靶向的纳米载药平台治疗RA滑膜炎研究新进展[J]. 新医学, 2024, 55(2): 101-105.Hu W H, Xu Y Z, Bai Z L, et al. Recent advances in macrophage-targeted nanoparticle drug delivery platforms for treating synovitis in rheumatoid arthritis[J]. New Med, 2024, 55(2): 101-105. [3] JIA M, REN W, WANG M, et al. Surface saturation of drug-loaded hollow manganese dioxide nanoparticles with human serum albumin for treating rheumatoid arthritis[J]. Drug Deliv, 2024, 31(1): 2380538. DOI: 10.1080/10717544. [4] YAN G, SONG R, ZHANG J, et al. MIF promotes Th17 cell differentiation in rheumatoid arthritis through ATF6 signal pathway[J]. Mol Med, 2024, 30(1): 237. DOI: 10.1186/s10020-024-01005-4. [5] 牛红青, 郝莉敏, 赵向聪, 等. 老年发病类风湿关节炎患者外周血CD4+T细胞亚群特征分析及临床意义[J]. 中华风湿病学杂志, 2025, 29(4): 301-306.Niu H Q, Hao L M, Zhao X C, et al. Changes and clinical significance of peripheral blood CD4+T cell subpopulations in patients with elderly-onset rheumatoid arthritis[J]. Chin J Rheumatol, 2025, 29(4): 301-306. [6] 中华医学会风湿病学分会. 类风湿关节炎诊断及治疗指南[J]. 中华风湿病学杂志, 2010, 14(4): 265-270.Rheumatology Branch of the Chinese Medical Association. Guidelines for diagnosis and treatment of rheumatoid arthritis[J]. Chin J Rheumatol, 2010, 14(4): 265-270. [7] 中华中医药学会风湿病分会. 类风湿关节炎病证结合诊疗指南[J]. 中医杂志, 2018, 59 (20): 1794-1800.Rheumatism Branch of China Association of Chinese Medicine. Guidelines for combined diagnosis and treatment of rheumatoid arthritis syndrome[J]. J Tradit Chin Med, 2018, 59(20): 1794-1800. [8] SHEEHY C, EVANS V, HASTHORPE H, et al. Revising DAS28 scores for remission in rheumatoid arthritis[J]. Clin Rheumatol, 2014, 33(2): 269-272. doi: 10.1007/s10067-013-2468-z [9] GARG U, JAIN N, KAUL S, et al. Role of albumin as a targeted drug carrier in the management of rheumatoid arthritis: a comprehensive review[J]. Mol Pharm, 2023, 20(11): 5345-5358. doi: 10.1021/acs.molpharmaceut.3c00581 [10] BIESEMANN N, MARGERIE D, ASBRAND C, et al. Additive efficacy of a bispecific anti-TNF/IL-6 nanobody compound in translational models of rheumatoid arthritis[J]. Sci Transl Med, 2023, 15(681): eabq4419. DOI: 10.1126/scitranslmed.abq4419. [11] 吕士金, 桑敏, 马强, 等. 不同证型类风湿性关节炎患者病情活动度的差异分析[J]. 四川中医, 2023, 41(5): 103-106.Lyu S J, Sang M, Ma Q, et al. Analysis of the difference of disease activity of rheumatoid arthritis of different TCM syndrome type[J]. J Sichuan Tradit Chin Med, 2023, 41(5): 103-106. [12] CHEN J, SHI X, DENG Y, et al. miRNA-148a-containing GMSC-derived EVs modulate Treg/Th17 balance via IKKB/NF-KappaB pathway and treat a rheumatoid arthritis model[J]. JCI Insight, 2024, 9(10): e177841. DOI: 10.1172/jci.insight.177841. [13] 周琴, 刘健, 孙艳秋, 等. 中药与类风湿关节炎合并低蛋白血症患者再入院风险降低的相关性: 一项回顾性队列研究[J]. 中国中药杂志, 2023, 48(8): 2241-2248.Zhou Q, Liu J, Sun Y Q, et al. Correlation between traditional Chinese medicine and reduced risk of readmission in rheumatoid arthritis patients with hypoproteinemia: a retrospective cohort study[J]. China J Chin Materia Med, 2023, 48(8): 2241-2248. [14] 曹跃朋. 类风湿关节炎患者外周血Th17/Treg细胞表达与中医证型相关研究[D]. 贵阳: 贵阳中医学院, 2014.Cao Y P. A study on the correlation between the expression of Th17/Treg cells in the peripheral blood of patients with rheumatoid arthritis and TCM syndrome types[D]. Guiyang: J Guiyang Coll Tradit Chin Med, 2014. [15] 刘丽敏, 秦理. 类风湿性关节炎中医证型与免疫功能、凝血功能指标的关系[J]. 辽宁中医杂志, 2023, 50(2): 84-87.Liu L M, Qin L. Relationship of TCM syndrome types, immune function and blood coagulation function index of rheumatoid arthritis patients[J]. Liaoning J Tradit Chin Med, 2023, 50(2): 84-87. [16] 王金凤, 黄海量, 刘杰, 等. 中药调控Th17/Treg平衡治疗类风湿关节炎的研究现状[J]. 中国药房, 2023, 34(6): 763-768.Wang J F, Huang H L, Liu J, et al. Research status of traditional Chinese medicine regulating Th17/Treg balance in the treatment of rheumatoid arthritis[J]. Chin Pharmacy, 2023, 34(6): 763-768. [17] ZHANG C, LU S, KANG T, et al. Red cell distribution width/albumin ratio and mortality risk in rheumatoid arthritis patients: insights from a NHANES study[J]. Int J Rheum Dis, 2024, 27(9): e15335. DOI: 10.1111/1756-185X.15335. [18] 王晓慧, 潘文萍, 孙素平, 等. 类风湿关节炎不同中医证型外周血Th17/Treg细胞表达特点研究[J]. 浙江中医杂志, 2018, 53(8): 549-550.Wang X H, Pan W P, Sun S P, et al. Study on the expression characteristics of Th17/Treg cells in peripheral blood of different TCM syndrome types of rheumatoid arthritis[J]. Zhejiang J Tradit Chin Med, 2018, 53(8): 549-550. [19] 宿家铭, 胡济源, 李思成, 等. 467例糖尿病肾脏病Ⅲ~Ⅳ期患者湿浊证证候分布规律及与临床特征的相关性研究[J]. 中华中医药杂志, 2024, 39(9): 4993-4997.Su J M, Hu J Y, Li S C, et al. Study on the distribution pattern of dampness-turbidity syndrome and its correlation with clinical characteristics in 467 cases of diabetic kidney disease stage Ⅲ-Ⅳ[J]. China J Tradit Chin Med Pharm, 2024, 39(9): 4993-4997. [20] 张坤, 陈彩娥. 类风湿关节炎患者中医证型特点与Th17/Treg平衡和疾病活动度的关系[J]. 四川中医, 2024, 42(10): 67-70.Zhang K, Chen C E. Relationship between TCM syndrome type and Th17/Treg balance and disease activity in patients with rheumatoid arthritis[J]. J Sichuan Tradit Chin Med, 2024, 42(10): 67-70.
 点击查看大图
计量
- 文章访问数: 7
- HTML全文浏览量: 3
- PDF下载量: 0
- 被引次数: 0
