



A case report of pseudohypoparathyroidism with epilepsy as the initial symptom
-
摘要: 假性甲状旁腺功能减退(PHP)是一种罕见的遗传性疾病,以低血钙、高血磷、高甲状旁腺激素为主要生化改变,其临床表现具有异质性。以癫痫为首发症状、无Albright遗传性骨营养不良(AHO)畸形的PHP患者极易被误诊。本文报道1例淮安市第一人民医院内分泌科收治的以癫痫起病的PHP病例,分析其临床资料、实验室检查、影像学检查和基因检测结果以及随访情况;并结合国内外相关文献进行复习,探讨PHP的临床特点和管理方案,以提高临床医生对该疾病的诊断和管理能力。
-
关键词:
- 假性甲状旁腺功能减退 /
- 癫痫 /
- 诊断 /
- 管理
Abstract: Pseudohypoparathyroidism (PHP) is a rare inherited disease, of which biochemical parameters show low blood calcium, high blood phosphorus, and high parathyroid hormone. The clinical manifestations of PHP are significantly heterogeneous. These PHP patients with epilepsy as the first symptom and without albright hereditary osteodystrophy (AHO) are easily misdiagnosed. This article selected one case of PHP with epilepsy from the Department of Endocrinology in the Huai'an No.1 People's Hospital. Its clinical data, laboratory tests, imaging examinations, genetic testing results, and follow-up were analyzed in combination with relevant literature at home and abroad. We aimed to explore the clinical characteristics and management strategies of PHP in order to improve the diagnostic and management abilities of clinical doctors for this disease.-
Key words:
- Pseudohypoparathyroidism /
- Epilepsy /
- Diagnosis /
- Management
-

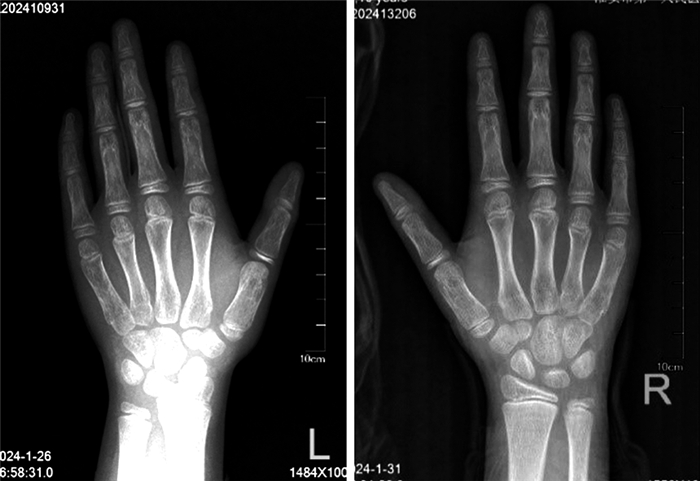
图 1 PHP患者双手(左手骨龄片)
Figure 1. The X-ray plain films of the PHP patient's hands (bone-age film)

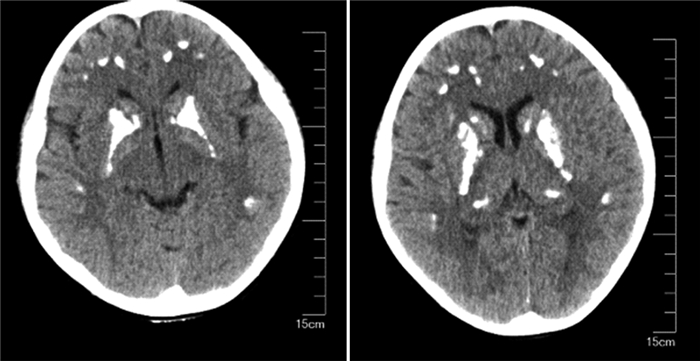
图 2 PHP患者头颅CT示双侧基底节区等多发钙化灶
Figure 2. The PHP patient's head CT shows multiple calcifications in the bilateral basal ganglia and other areas
表 1 患者实验室检查结果
Table 1. The result of patients' laboratory examinations
日期 PTH(pg/mL) 血钙(mmol/L) 血磷(mmol/L) 总25羟维生素D(ng/mL) 甲状腺功能 性激素 2024年1月27日 242.00 1.36 3.33 未测 正常、TRAb、TPOAb E2<5.000 pg/mL,FSH 0.46 IU/L TG-Ab阴性 LH<0.300 IU/L,T<0.087 nmol/L,PRL 2.21 ng/mL 2024年1月28日 未测 1.52 3.23 16.16 未测 未测 2024年3月11日 134.00 2.31 2.11 未测 未测 未测 2024年4月16日 203.50 2.30 2.09 29.90 未测 未测 注:血钙正常范围2.10~2.70 mmol/L;血磷正常范围0.81~1.45 mmol/L;TRAb为促甲状腺激素受体抗体(thyrotropin receptor antibodies);TPOAb为抗甲状腺过氧化物酶抗体(thyroperoxidase antibodies);TG-Ab为抗甲状腺球蛋白抗体(antithyroglobulin antibodies);E2为雌二醇(estradiol);FSH为卵泡生成素(follicle stimulating hormone),正常参考范围为1.50~14.40 IU/L;LH为促黄体生成素(luteinizing hormone);T为睾酮(testosterone);PRL为垂体泌乳素(pituitary prolactin),正常参考范围为4.04~15.20 ng/mL。  下载: 导出CSV
表 2 患者生长激素兴奋试验结果(ng/mL)
Table 2. The result of patients' growth hormone stimulation test (ng/mL)
生长激素兴奋试验 0 min 30 min 60 min 90 min 120 min 精氨酸激发实验 0.09 5.79 4.33 1.16 0.40 左旋多巴激发实验 0.13 0.21 7.03 9.23 2.32
下载: 导出CSV
-
[1] NAGANUMA J, SUZUMURA H, KOYAMA S, et al. Pseudohypoparathyroidism type 1B with involuntary movements: a case report and literature review[J]. Clin Pediatr Endocrinol, 2024, 33(3): 151-156. doi: 10.1297/cpe.2023-0080 [2] MADURO A I, PINTO SARAIVA A, PIMENTA RODRIGUES O, et al. Albright's hereditary osteodystrophy: an entity to recognize[J]. Rheumatology (Oxford), 2022, 61(11): e356-e357. DOI: 10.1093/rheumatology/keac277. [3] 简丽, 蔡勇, 何阳杰, 等. 假性甲状旁腺功能减退症Ⅰa型合并急性脑卒中1例及文献回顾[J]. 中华全科医学, 2021, 19(9): 1608-1611. doi: 10.16766/j.cnki.issn.1674-4152.002123Jian L, Cai Y, He Y J, et al. A case of pseudohypoparathyroidism type Ia combined with acute stroke and literature review[J]. Chinese Journal of General Practice, 2021, 19(9): 1608-1611. doi: 10.16766/j.cnki.issn.1674-4152.002123 [4] 赵子暄, 权莉, 蒋升. 假性甲状旁腺功能减退症的临床进展[J]. 新疆医学, 2023, 53(6): 657-659.Zhao Z X, Quan L I, Jiang S. Clinical progress of pseudohypoparathyroidism[J]. Xinjiang Medical Journal, 2023, 53(6): 657-659. [5] JANUŚ D, ROZTOCZYŃSKA D, JANECZKO M, et al. New insights into thyroid dysfunction in patients with inactivating parathyroid hormone/parathyroid hormone-related protein signalling disorder (the hormonal and ultrasound aspects): one-centre preliminary results[J]. Front Endocrinol (Lausanne), 2022, 13: 1012658. DOI: 10.3389/fendo.2022.1012658. [6] SLOUMA M, HANNECH E, GHARSALLAH I. Hypoparathyroidism: musculoskeletal manifestations related to parathormone deficiency[J]. Curr Rheumatol Rev, 2024, 20(5): 488-500. doi: 10.2174/0115733971267895231227102539 [7] 杨文君, 龙晓丹, 莫朝晖, 等. GNAS基因突变致2例假性甲状旁腺功能减退症Ⅰa型[J]. 中华骨质疏松和骨矿盐疾病杂志, 2021, 14(6): 601-606.Yang W J, Long X D, Mo C H, et al. Two cases of pseudohypoparathyroidism type Ⅰa caused by GNAS gene mutation[J]. Chin J Osteoporos Bone Miner Res, 2021, 14(6): 601-606. [8] EXPÓSITO RASPEÑO M, SÁNCHEZ ESCUDERO V, PÉREZ DE NANCLARES LEAL G, et al. Diagnosis and approach of pseudohypoparathyroidism type 1A and related disorders during long term follow-up: a case report[J]. J Pediatr Endocrinol Metab, 2024, 37(3): 289-295. doi: 10.1515/jpem-2023-0454 [9] URAKAWA T, SANO S, KAWASHIMA S, et al. (Epi)genetic and clinical characteristics in 84 patients with pseudohypoparathyroidism type 1B[J]. Eur J Endocrinol, 2023, 189(6): 590-600. doi: 10.1093/ejendo/lvad163 [10] LUO D D, QI X Y, LIU L N, et al. Genetic and epigenetic characteristics of autosomal dominant pseudohypoparathyroidism Type 1B: case reports and literature review[J]. Horm Metab Res, 2021, 53(4): 225-235. doi: 10.1055/a-1341-9891 [11] YOON S H, MEYER M B, AREVALO C, et al. A parathyroid hormone/salt-inducible kinase signaling axis controls renal vitamin D activation and organismal calcium homeostasis[J]. J Clin Invest, 2023, 133(9): e163627. DOI: 10.1172/JCI163627. [12] JÜPPNER H. Molecular definition of pseudohypoparathyroidism variants[J]. J Clin Endocrinol Metab, 2021, 106(6): 1541-1552. doi: 10.1210/clinem/dgab060 [13] 范娟, 高升波, 魏玉娇, 等. 终末期肾病病人骨桥蛋白水平与冠状动脉钙化相关性[J]. 青岛大学学报(医学版), 2021, 57(4): 517-521.Fan J, Gao S B, Wei Y J, et al. Relationship between osteopontin level and coronary artery calcification in patients with end-stage renal disease[J], J of Qindao University(Medical sciences), 2021, 57(4): 517-521. [14] 马海燕, 朱海涛, 杨露, 等. 以癫痫样发作为主要表现的甲状旁腺功能减退症的临床特征分析[J]. 临床神经病学杂志, 2023, 36(3): 165-169.Ma H Y, Zhu H T, Yang L, et al. Analysis of clinial features of hypoparathyroidism with epileptiform as the main manifestation[J], J Clin Neurol, 2023, 36(3): 165-169. [15] 迟秀娥, 张倩, 李文东, 等. 误诊为癫痫的假性甲状旁腺功能减退症Ⅰa型1例并文献复习[J]. 临床荟萃, 2022, 37(9): 827-830.Chi X E, Zhang Q, Li W D, et al. Pseudohypoparathyroidism type Ⅰa misdiagnosed as epilepsy: a case report and literatures review[J]. Clinal Focus, 2022, 37(9): 827-830. [16] ABBAS A, HAMMAD A S, AL-SHAFAI M. The role of genetic and epigenetic GNAS alterations in the development of early-onset obesity[J]. Mutat Res Rev Mutat Res, 2024, 793: 108487. DOI: 10.1016/j.mrrev.2023.108487.
 点击查看大图
计量
- 文章访问数: 7
- HTML全文浏览量: 4
- PDF下载量: 0
- 被引次数: 0
